If your surgeon has told you the cartilage in your ankle is gone, or used the phrase "bone on bone," you are probably weighing two operations. Ankle fusion permanently joins your leg bone to your ankle bone so the painful joint stops moving. Ankle replacement removes the worn surfaces and puts in a metal and plastic implant so the joint keeps moving.
You have likely already been told two things: that replacement keeps your motion, and that fusion wears out the rest of your foot. Both are repeated everywhere, and both are less true than they sound. The motion you get back from a replacement is usually small. And the largest study ever done on this question, following more than 41,000 people for 25 years, found that the chance of eventually needing another joint in your foot fused was about the same either way.
So the real question is not which operation is better. It is which one fits your ankle, your age, and what you need your foot to do for your activities. This guide covers both, and spends real time on the things people actually want to know: whether you will limp, when you can drive, when you can get back to work, and what you will and will not be able to do afterward.
Quick facts about ankle fusion and ankle replacement
- Why you have this: Most ankle arthritis comes from an old fracture or bad sprain, not ordinary aging, which is why many patients are in their 40s and 50s
- Back in a normal shoe: Around 8 weeks after replacement, usually closer to 12 weeks after fusion
- Driving again: Roughly 8 weeks after a replacement on the right ankle, and closer to 3 to 4 months after a fusion
- Back to work: About 2 weeks for a desk job, up to 12 weeks if you are on your feet all day
- How long a replacement lasts: About 89 out of 100 implants are still working at 10 years
- Which needs redoing more often: Replacement, at roughly 10 percent by 10 years, compared with about 2.5 percent for fusion
As Arush K. Angirasa, DPM, FACFAS, a board-certified podiatric surgeon specializing in lower extremity trauma and reconstructive surgery, I have this conversation regularly across our Central Texas clinics. It is usually with someone who broke an ankle fifteen or twenty years ago and has quietly worked around it ever since. What I tell them first is that this decision is almost never made on the ankle alone. It comes down to how your whole leg lines up, what the joints just below your ankle look like, and how much bone we have to work with.
Why your ankle wore out, and why that matters here
Hip and knee arthritis is usually just wear and tear over decades. Ankle arthritis is different. The large majority of cases are post-traumatic, meaning they trace back to a fracture or a severe ligament injury that left the joint sitting a few millimeters off.
The ankle fits together very tightly, which is normally a strength. But when it is slightly out of line, all your body weight gets funneled onto a small patch of cartilage instead of spread across the whole surface. That patch wears through, and fifteen years after an injury you had mostly forgotten about, the joint gives out.
This matters for your decision in a very practical way. Because the cause was an injury rather than age, you may be considerably younger than the typical hip or knee replacement patient. You may have thirty or forty years of walking ahead of you, and you may still be doing physical work. An implant has a limited lifespan. A fusion does not. That single fact drives a lot of what follows.
What causes it
- A previous fracture, especially one that went through the joint surface itself. This is the most common cause by a wide margin.
- Repeated or severe sprains, which leave the ankle unstable so it shifts slightly with every step
- Rheumatoid arthritis and related inflammatory conditions, which attack the joint lining directly
- Foot shape, since a high arch or a flat foot tilts the ankle and loads one side harder than the other
- Loss of blood supply to the talus, the ankle bone, which can cause the joint surface to collapse
Signs your arthritis has reached the point where surgery gets discussed
- Pain at rest and at night, not just when you are active. This is the clearest sign the cartilage is genuinely gone.
- Trouble on hills and stairs, and difficulty pushing off when you walk
- Swelling that no longer goes down overnight
- Grinding or catching as bare bone meets bare bone
- A visible tilt to the ankle when you stand
What your surgeon checks before recommending one or the other
- Where the pain is actually coming from. Ankle arthritis and arthritis in the joints just below the ankle feel very similar to patients. Sometimes the cleanest way to tell them apart is a small numbing injection into one specific joint to see what it takes away.
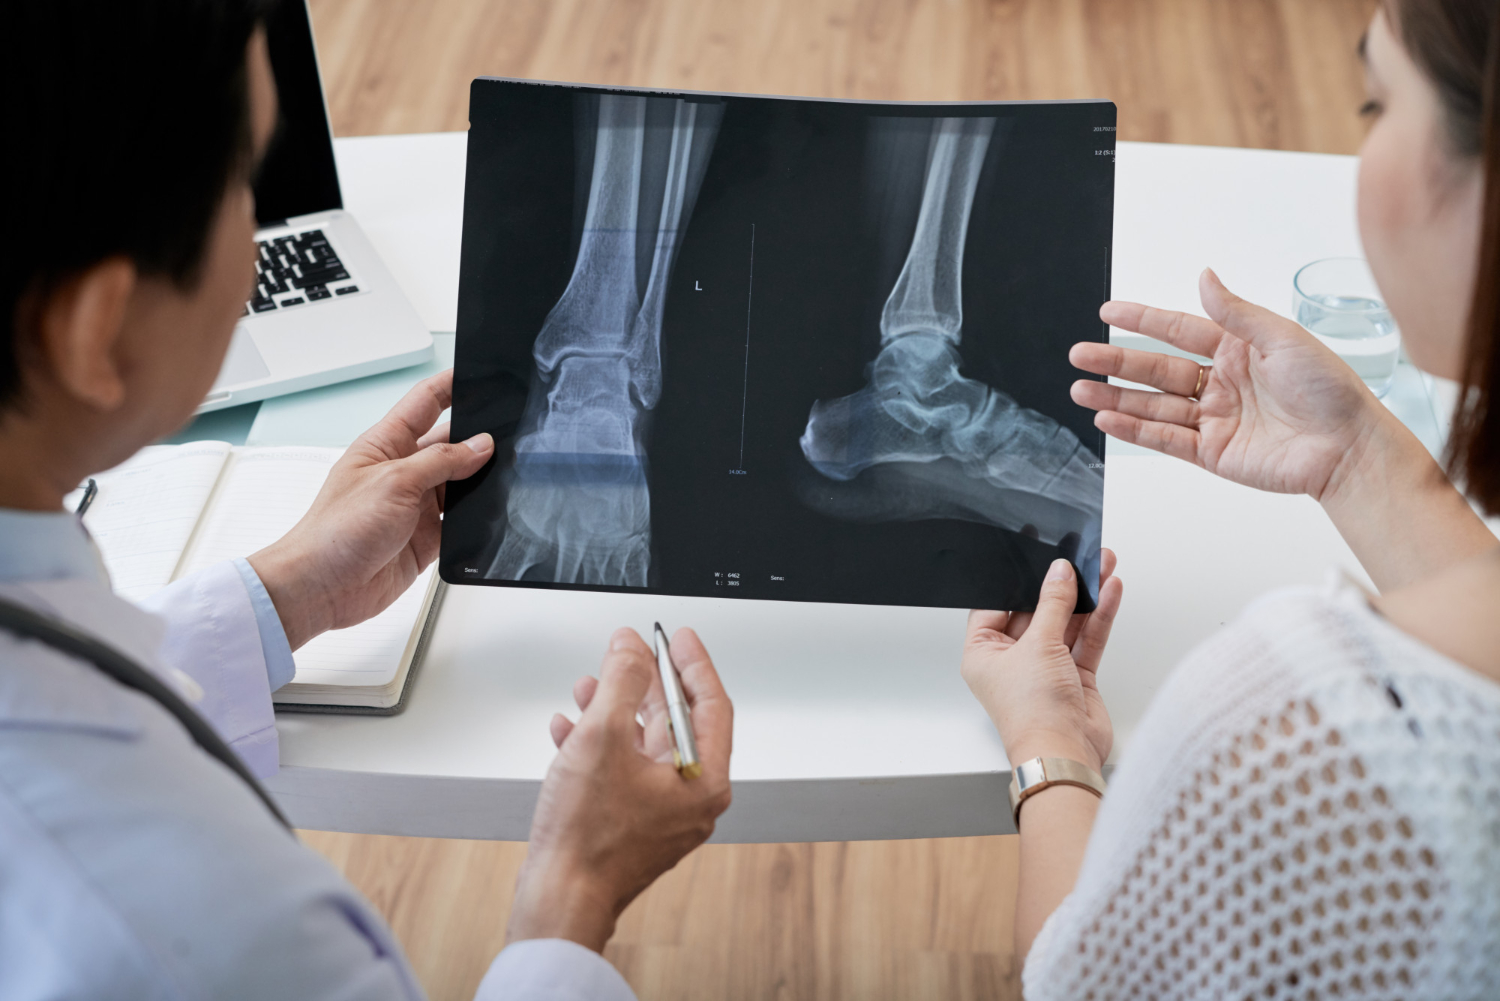
- Standing X-rays. These have to be taken while you are bearing weight. A badly tilted ankle can look almost normal on an X-ray taken lying down, because the deformity only shows up under load. If you have only ever had X-rays lying down, that is worth raising.
- A CT scan. This shows how solid your bone is, whether cysts have formed, and what condition the joints below the ankle are in. It is the main planning tool if a replacement is being considered.
- An MRI, used when there is concern about the blood supply to the ankle bone or when the pain pattern does not add up.
The two operations, side by side
| Question | Ankle fusion | Ankle replacement |
|---|---|---|
| What is done | Worn surfaces are removed and the bones are held together with screws or plates until they grow into one solid bone | Worn surfaces are removed and replaced with metal parts and a plastic bearing in between |
| Motion afterward | None at the ankle. The smaller joints in your foot take over some of the movement. | Kept, though the gain is usually modest rather than dramatic |
| Normal shoe at | Around 12 weeks | Around 8 weeks |
| Driving again | Roughly 3 to 4 months for the right ankle | Roughly 8 weeks for the right ankle |
| Needs redoing | About 2.5 percent by 10 years | About 10 percent by 10 years |
| Main thing that goes wrong | The bones fail to knit together. Around 7 in 100 had a painful nonunion in the best trial available. | The implant loosens or wears out over time |
| Usually better for | Younger or heavier patients, physical jobs, significant deformity, softer bone, past infection, nerve damage from diabetes | Older and less physically demanding patients, well-aligned ankles, good bone, stiff joints below the ankle, arthritis in both ankles |
Ankle fusion
Fusion has been the dependable option for a century. It can sometimes be done through small incisions when your ankle is well aligned, or as an open operation when deformity needs correcting. Because there is no implant, there is nothing to wear out, which is why it needs redoing so much less often. You can read more on our ankle arthrodesis page.
Ankle replacement
Implants have improved a great deal over several generations, and modern ones are placed with guides made from your own CT scan, so they sit more accurately than older systems did. A replacement keeps the joint moving and tends to give a more natural walking pattern. The tradeoffs are that it has a finite lifespan, redoing it is harder than doing it the first time, and it is much less forgiving of a crooked ankle or soft bone. Details are on our ankle joint replacement page.
What life is actually like afterward
This is the part most people want and rarely get. Every ankle is different and your surgeon's protocol may vary, but here is the realistic picture.
Will you limp?
Less than you are probably imagining, particularly after a fusion. Most people assume a fused ankle means an obvious hitch in their walk. In practice the midfoot picks up a surprising amount of the motion, and on flat ground most people walk well enough that others do not notice. Where you will notice it is on slopes, stairs, ladders, and uneven ground like a gravel driveway or a hiking trail. A replacement generally gives a smoother, more normal gait.
When can you drive?
If it is your left ankle and you drive an automatic, often quite early, sometimes within a few weeks. If it is your right ankle, plan on around 8 weeks after a replacement and closer to 3 to 4 months after a fusion. You need to be out of the boot and able to brake hard without hesitating. This is worth planning around, because it is the restriction that catches people off guard.
When can you go back to work?
The first two weeks are non-negotiable regardless of what you do, because keeping the foot elevated in that window has a real effect on how the wound heals. After that it depends entirely on the job. Desk work with the ability to elevate your leg is often possible at around 2 weeks. If you are on your feet all day, climbing, or required to wear dress shoes, expect closer to 12 weeks.
What shoes can you wear?
Most people get back into ordinary shoes. After a fusion, a shoe with a slightly rounded or rocker sole makes a noticeable difference, because it rolls you through the step that your ankle can no longer do itself. Cushioned, supportive shoes are more comfortable than flat, thin-soled ones. High heels are generally not realistic after either operation.
What can you still do?
Walking, hiking on reasonable terrain, cycling, swimming, and golf are all typically fine after either operation, and many people do more afterward than they did in the painful years beforehand. Running and repeated impact are generally discouraged, after a replacement because it shortens implant life, and after a fusion because the joints picking up the slack take the punishment. Standing on a ladder is harder after a fusion. If your job or your hobbies depend on that, say so early, because it should influence the recommendation.
Two things you have probably been told that need correcting
"A replacement will give you your motion back." It keeps motion, which is a real advantage, but the amount actually gained is often small. Many people end up with a joint that moves a little more than before and hurts a lot less. If you are picturing an ankle that bends like it did at twenty, adjust that expectation now rather than at the three-month visit.
"Fusion will destroy the rest of your foot." This comes from older studies that looked at X-rays and found changes in neighboring joints in more than 80 percent of people. But a change visible on an X-ray is not the same thing as pain that needs an operation. The 25-year study of more than 41,000 patients found that the number who actually went on to need another joint fused was 8.6 percent after a fusion and 6.8 percent after a replacement, which is not a meaningful difference.
There is one more thing worth knowing. The only study that took a large group of patients and randomly assigned them to one operation or the other, the TARVA trial, followed 303 people and found that both groups were walking and standing substantially better a year later, with no clear winner between them. That is genuinely reassuring. Whichever operation is right for your ankle, the odds of being much better off in a year are good.
Who tends to do better with each
Fusion usually makes more sense if you are younger and expect decades of hard use, if you work on ladders or uneven ground, if your ankle is significantly tilted, if your bone is soft, if you have had a deep infection in that ankle before, if you have nerve damage from diabetes, or if your weight would load an implant heavily.
Replacement usually makes more sense if you are older with lower physical demands, if your ankle is well aligned with good solid bone, if the joints below your ankle are already stiff or arthritic and cannot take on extra work, or if both ankles are affected, since fusing both is poorly tolerated.
Either way, surgery is not the first step. Bracing, activity changes, anti-inflammatory medication, weight management, and joint injections can control symptoms for years, and at least six months of that is standard before an operation is considered. If you have already been through it and you are still in pain, you can book a foot and ankle evaluation online or call 512-266-3377.
Recovery, week by week
- Weeks 0 to 2. Splint or cast, foot elevated most of the day, no weight on it. This is the window that matters most for wound healing, and it is worth being strict.
- Weeks 2 to 6. Stitches out and into a cast or boot. Still no weight on the foot for most fusions. Some replacement protocols start gentle motion here to keep the joint from stiffening.
- Weeks 6 to 12. Weight gradually comes back once X-rays show healing. Replacement patients are usually cleared earlier in this stretch than fusion patients, who often stay in a boot until union is confirmed at around 12 weeks.
- Months 3 to 6. Out of the boot and into supportive shoes. Physical therapy focuses on calf strength, balance, and relearning a normal walking pattern, which takes more retraining than people expect after months of limping.
- Months 6 to 12. Most people reach their new normal somewhere between nine and twelve months. Swelling at the end of a long day can last a full year and does not mean anything is wrong.
Frequently asked questions
Is ankle fusion or ankle replacement better?
Neither is better across the board, which is why this decision takes a real conversation. When researchers randomly assigned 303 patients to one or the other, both groups were walking and standing much better a year later with no clear difference between them. Fusion needs redoing less often. Replacement keeps your motion and gives a more natural gait. The right answer depends on your age, weight, alignment, bone quality, and the condition of the joints below your ankle.
Will I limp after an ankle fusion?
Usually less than you expect. The smaller joints in your foot compensate for the motion the ankle no longer has, and on level ground most people walk well enough that it is not obvious. Hills, stairs, ladders, and uneven ground are where you notice it. A shoe with a rounded sole helps a great deal.
When can I drive after ankle fusion or replacement?
If it is your left ankle and you drive an automatic, often within a few weeks. For the right ankle, plan on roughly 8 weeks after a replacement and 3 to 4 months after a fusion. You need to be out of the boot and able to brake in an emergency without hesitating.
How long does an ankle replacement last?
About 89 out of 100 modern implants are still in place at 10 years. Over 20 years, registry data puts the chance of needing it redone at roughly 13 or 14 percent. Implant lifespan is the main reason replacement is approached carefully in younger, heavier, or physically demanding patients.
Can I still hike or play golf afterward?
Generally yes, for both operations. Walking, hiking, cycling, swimming, and golf are all typically fine, and many people do more once the pain is gone than they did in the years before surgery. Running and repeated impact are usually discouraged. Uneven trails are harder after a fusion than after a replacement.
Does ankle fusion wear out the other joints in my foot?
Less than the old figures suggest. Older studies found changes on X-rays in over 80 percent of patients, but an X-ray change is not the same as pain that needs surgery. The largest study available, following more than 41,000 patients for 25 years, found that 8.6 percent needed another joint fused after a fusion compared with 6.8 percent after a replacement, which is not a meaningful gap.
Schedule a foot and ankle consultation at BoneDrs
Ankle pain that wakes you up at night, or that has started changing how you walk, is worth having properly evaluated with standing X-rays. Choosing between fusion and replacement is one of the bigger decisions in foot and ankle surgery, and it should be made with your own alignment, bone quality, and daily life in front of you rather than from general rules.
Our foot and ankle team sees patients in Austin, San Marcos, Round Rock, and Bastrop, and offers everything from bracing and injections through both fusion and replacement. Book an appointment online in about a minute, or call 512-266-3377.
If you have any concerns about your joints, contact us and we can help determine a treatment that works for you.